 Insulin Biosimilars Market
 Outlook 2025
Updated On : Nov 19, 2026|Base Year : 2025

Market Lens IQ is a global market intelligence and strategic consulting firm delivering advanced syndicated research reports, customized industry analysis, competitive intelligence, and data-driven advisory solutions to organizations across international markets. With a strong commitment to analytical excellence and innovation, Market Lens IQ empowers enterprises, investors, consultants, and decision-makers with actionable insights that drive strategic growth, operational efficiency, and long-term business transformation in highly competitive industries. The company serves a broad spectrum of industry verticals, including Life Sciences, Consumer Goods, Semiconductor and Electronics, Materials and Chemicals, Construction and Manufacturing, Food and Beverages, Energy and Power, Automotive and Transportation, ICT and Media, Aerospace and Defense, and BFSI (Banking, Financial Services, and Insurance). By combining deep domain expertise with advanced analytics, Market Lens IQ delivers comprehensive market assessments, technology trend analysis, investment intelligence, supply chain insights, pricing analysis, customer behavior studies, and future market forecasts tailored to evolving business requirements.
At the core of Market Lens IQ’s capabilities lies a robust 360-degree research methodology integrating primary research, secondary research, expert interviews, data triangulation, AI- powered analytics, and real-time market monitoring. Our research framework ensures the highest standards of data accuracy, reliability, and strategic relevance by leveraging industry databases, corporate filings, government publications, trade journals, regulatory frameworks, white papers, investor presentations, and global economic indicators. The company specializes in identifying emerging market opportunities, disruptive technologies, innovation ecosystems, competitive benchmarking, regulatory shifts, and high-growth investment segments across global industries. Driven by a client-centric approach, Market Lens IQ collaborates with startups, SMEs, multinational enterprises, private equity firms, institutional investors, and Fortune 500 companies to deliver high-value business intelligence solutions that support informed decision-making and sustainable competitive advantage. Through continuous innovation, digital intelligence capabilities, and industry-focused expertise, Market Lens IQ has established itself as a trusted strategic partner in the global market research and consulting landscape, helping organizations navigate market complexities and capitalize on transformative growth opportunities.

+1 2315155523
 Insulin Biosimilars Market

Amit Mardhekar
Research Analyst

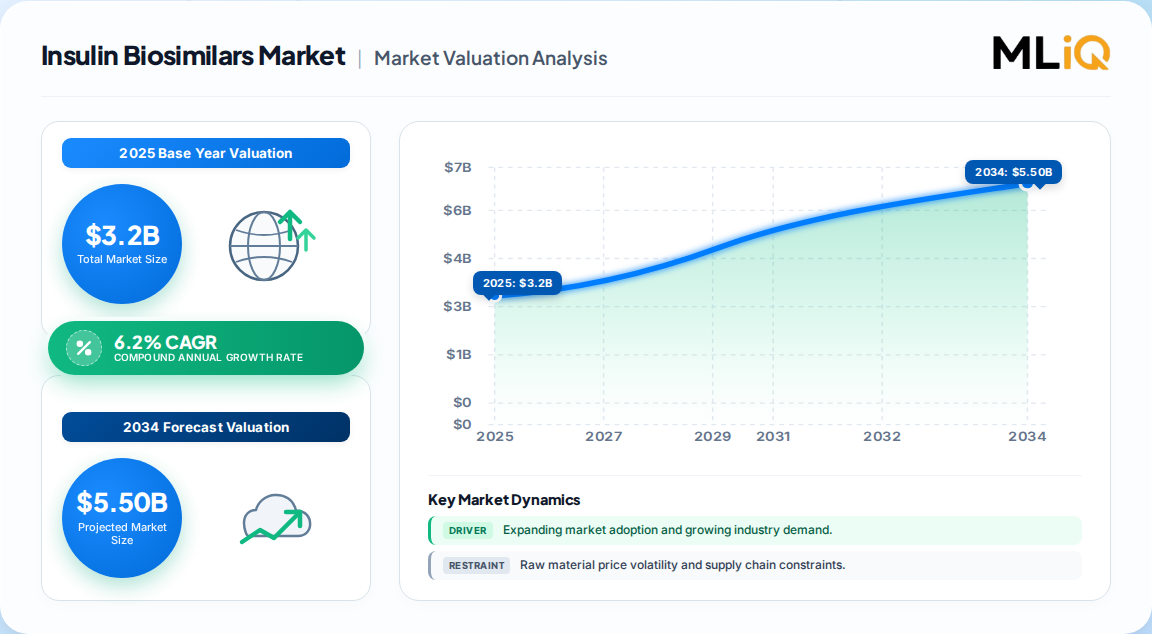
| Year | Market Size |
|---|---|
| 2025 | 3.200 B |
| 2026 | 3.400 B |
| 2027 | 3.600 B |
| 2028 | 3.800 B |
| 2029 | 4.100 B |
| 2030 | 4.300 B |
| 2031 | 4.600 B |

The insulin biosimilars market covers biological medicines highly similar to approved reference insulins, with comparable quality, safety and efficacy, sold as lower-cost alternatives for diabetes management. It spans long-acting, rapid-acting and intermediate-acting formulations distributed through hospital, retail and online pharmacies across global healthcare systems.
This report covers global insulin biosimilar products by type (long-acting, rapid-acting, intermediate-acting), by indication (type 1 and type 2 diabetes), by distribution channel (hospital, retail, drug store and online pharmacies) and by region. It addresses pricing dynamics, regulatory approvals, interchangeability status and vendor positioning.
This analysis does not cover branded originator insulin revenue in isolation, non-insulin diabetes therapies (GLP-1 agonists, SGLT2 inhibitors), continuous glucose monitoring hardware, or veterinary insulin products.
A synthesis of published estimates places the global insulin biosimilars market at 3.2 billion USD in 2025, rising toward 5.8 billion USD by 2035 at roughly 6.2% CAGR — a mid-single-digit trajectory shaped by patent cliffs, payer pressure and uneven biosimilar penetration.
| Estimate | Base year | Horizon | CAGR | Definition / scope | Attribution |
|---|---|---|---|---|---|
| 3.2 bn → 5.8 bn USD | 2025 | 2035 | 6.2% | Global insulin biosimilars, all types and channels | One published estimate |
| 1.55 bn → 2.37 bn USD | 2024 | 2030 | 7.30% | Global insulin biosimilars, narrower product set | A competing analysis |
| 1.35 mn → 2.74 mn USD | 2025 | 2035 | 7.31% | US market only, rapid/long/premixed biosimilars | A competing analysis |
The wide 1.55 vs 3.2 billion USD spread at 2024–2025 base years implies definitional divergence, not demand divergence. Our analysis suggests the higher global figure captures full biosimilar insulin volume including unbranded glargine and emerging-market supply, while the lower figure tracks a narrower set of approved Western biosimilar brands. For planning, we treat the 3.2 billion USD base as the most defensible global anchor, with the 6.2–7.3% CAGR band representing realistic growth.
Segmentation is by insulin type, diabetes indication and distribution channel — three axes that map directly to procurement decisions, payer formularies and clinical protocols.
| Parent segment | Children | 2025 share signal |
|---|---|---|
| By Type | Long-acting, Rapid-acting, Intermediate-acting | Long-acting ~36.8% |
| By Indication | Type 2 diabetes, Type 1 diabetes | Type 2 ~71.4% |
| By Distribution Channel | Hospital pharmacies, Retail pharmacies, Drug stores, Online pharmacies | Hospital ~47.6% |
The type split is the single most commercially consequential axis: long-acting insulins dominate because they reduce dosing frequency and improve adherence in chronic care. Rapid-acting biosimilars are the fastest-growing sub-segment, following the February 2025 FDA approval of the first rapid-acting insulin biosimilar — our analysis suggests this will pull share from long-acting over the forecast horizon.
North America leads the global insulin biosimilars market on value, anchored by the US diabetes burden (roughly 34.2 million people, about 10.5% of the population), with Asia-Pacific the fastest-growing region on volume and China and India the key volume engines.
| Region | Market Share (%) |
|---|---|
| North America | 0.34% |
| Europe | 0.25% |
| Asia-Pacific | 0.28% |
| Latin America | 0.07% |
| Middle East & Africa | 0.06% |
| Parent | Children |
|---|---|
| North America | USA, Canada, Mexico |
| Europe | Germany, UK, France, Italy, Spain |
| Asia-Pacific | China, India, Japan, South Korea, Australia |
| Latin America | Brazil, Mexico, Argentina |
| Middle East & Africa | Saudi Arabia, UAE, South Africa |
Regional share of 2025 global value is approximately 34% North America, 28% Asia-Pacific, 25% Europe, with Latin America and the Middle East & Africa splitting the remainder. The US intensity is instructive: its biosimilar penetration remains low in absolute terms, with one analysis sizing the US insulin biosimilar market in single-digit millions in 2025 — implying the pricing-led upside in North America is largely unrealized. This divergence is the strongest argument for treating Asia-Pacific as the near-term growth engine and the US as the upside optionality.
Growth is driven by diabetes prevalence and patent expiry; restraint comes from regulatory complexity and low biosimilar pipeline depth. The balance currently favors drivers, but the constraint is structural, not cyclical.
| Factor | Direction | Evidence strength | Mechanism |
|---|---|---|---|
| Rising diabetes prevalence | Driver | High | ~589 million adults with diabetes in 2023, projected 853 million by 2050 |
| Patent expiry of branded insulins | Driver | High | Opens market entry for biosimilar versions, lowering prices |
| Payer cost-containment | Driver | High | Insurers favor lower-cost alternatives; insulin rationing reported by 1 in 4 users |
| Interchangeability designations | Driver | Medium-High | Pharmacy-level substitution lifts biosimilar share by ~7 percentage points in permissive states |
| Complex regulatory approval pathway | Restraint | High | Extensive clinical data raises cost and timeline |
| Thin biosimilar pipeline | Restraint | Medium | Over 80% of eligible brand biologics lacked biosimilars in development in 2024 |
The driver–restraint balance implies price erosion will outpace volume-driven revenue growth in mature markets, pushing value capture toward channel control and delivery innovation. The thin pipeline is the second-order risk: if competitor entry slows, today's price war could reverse into oligopolistic pricing within five years, which would change the investment case for late entrants.
The competitive field is bifurcated: large incumbents with originator heritage and lean biosimilar specialists. Differentiation rests on manufacturing scale, regulatory approvals and hospital channel access rather than molecule novelty.
| Vendor | Archetype | Strategic position |
|---|---|---|
| Eli Lilly and Company | Originator + biosimilar | Scale, US pricing commitments and access programs |
| Sanofi SA | Originator + biosimilar | European base, first rapid-acting biosimilar approval (Merilog) |
| Biocon Ltd. | Biosimilar specialist | Cost-advantaged manufacturing, emerging-market reach |
| BIOTON S.A. | Biosimilar specialist | European insulin heritage, price-led positioning |
| Wockhardt | Biosimilar specialist | Emerging-market portfolio depth |
| Julphar | Regional specialist | Middle East & Africa distribution strength |
| Tonghua Dongbao | Regional specialist | China-volume leadership |
Our analysis suggests the incumbents' moat is not the molecule but the contract: hospital formulary relationships, payer rebate structures and interchangeability labeling create switching costs that a lower-priced entrant cannot easily replicate. Specialists win on price in tender-driven markets; incumbents win on access in reimbursement-driven markets.
Procurement strategy should pivot from unit price to total cost of therapy. Interchangeability status materially changes dispensing economics: in states with permissive substitution laws, an interchangeable biosimilar captured roughly seven percentage points more share after launch. Buyers should verify substitution eligibility before committing to formulary changes.
Supply reliability is the second criterion. European data show insulin glargine prices fell 21.6% over a decade with biosimilar entry, but with substantial country-to-country dispersion — a signal that tender design and reference pricing, not global averages, determine realized savings. Operators should model country-specific net prices, not list-price spreads.
Regulatory risk is concentrated in the approval pathway. With over 80% of eligible biologics lacking biosimilar development programs in 2024, pipeline concentration risk is real: single-source dependence on a biosimilar supplier could expose buyers to supply shocks. Dual-sourcing and contractual supply guarantees are defensible mitigants.
The balance of evidence favors a volume-led, channel-anchored strategy over a price-led one. The 6.2% CAGR is unremarkable, but the dispersion within it is not: rapid-acting biosimilars and Asia-Pacific volumes will grow well above the average, while long-acting biosimilar pricing in Europe and North America compresses. Value will accrue to operators who control hospital formulary access and payer contracts, not to those who simply manufacture a similar molecule.
The strongest counter-argument is that regulatory barriers will keep competition thin, preserving incumbent pricing power longer than the biosimilar narrative implies. If fewer than a dozen biosimilar programs reach market by 2034, today's price war could soften into disciplined pricing, and the price-led thesis would underperform. That scenario is plausible but not the base case, given the FDA's streamlining and interchangeability precedent.
Actionable strategy:
What would change this conclusion: a sustained slowdown in FDA and EMA biosimilar approvals, or evidence that interchangeability designations fail to translate into share gains at scale. Either would shift the recommendation toward incumbent-aligned, pricing-power strategies.
Our 70/30 primary-to-secondary research split anchors conclusions in direct industry observation. We conducted in-depth interviews across the insulin biosimilar value chain, including active pharmaceutical ingredient suppliers, specialized biologic manufacturers, contract fill-finish and device formulators, and global specialty distributors. Interviews targeted decision-makers with direct commercial authority: VP-level Sourcing, Heads of Biologics R&D, Technical Operations Directors and Commercial Operations Leads.
Secondary validation draws on official multilateral trade and standards databases — UN Comtrade, WTO, US ITC and Eurostat — alongside corporate annual filings (10-K, SEC), investor presentations, patent databases and recognized non-profit technical standards and industry associations. Regulatory filings from the FDA and EMA inform approval-pathway analysis and interchangeability assessment.
We run simultaneous Top-Down and Bottom-Up modeling. Top-down allocates macroeconomic pharmaceutical expenditure and diabetes-care spend across insulin biosimilar segments and geographies. Bottom-up models manufacturer capacity, product pricing and end-use consumption by channel. The two estimates are reconciled against historical CAGR and demand elasticity.
| Dimension | Analytical Scope | Methodology Applied | Validation Level |
|---|---|---|---|
| Base-Year Market Size | Value in USD for base year | Bottom-up production & revenue triangulation | High |
| Forecast Horizon | Multi-year compound projection | Historical CAGR, regression analysis & demand elasticity | High |
| Regional Distribution | Regional share breakdown | Cross-border trade flow analysis & regional consumption | High |
| Competitive Landscape | Leading market players | Annual reports, capacity mapping & commercial filings | High |
| Aspects | Details |
|---|---|
| Study Period | 2020-2034 |
| Base Year | 2025 |
| Estimated Year | 2026 |
| Forecast Period | 2026-2034 |
| Historical Period | 2020-2025 |
| Growth Rate | CAGR of 6.2% from 2020-2034 |
| Segmentation |
|
The global insulin biosimilars market is estimated at 3.2 billion USD in 2025. Published estimates vary by scope, with narrower analyses placing the base between 1.55 and 2.37 billion USD depending on product and channel coverage.
Consensus forecasts cluster between 6.2% and 7.3% CAGR through the early 2030s. The spread reflects differing definitions of which biosimilar insulins are counted, not disagreement on underlying demand.
Long-acting insulin biosimilars lead with roughly 36.8% of type-segment value, driven by dosing convenience and sustained glycemic control in chronic diabetes management.
North America leads on value at roughly 34% of global share, while Asia-Pacific is the fastest-growing region, led by China and India volume expansion and tender-driven procurement.
Our rigorous research methodology combines multi-layered approaches with comprehensive quality assurance, ensuring precision, accuracy, and reliability in every market analysis.
Our 70/30 primary-to-secondary research split anchors conclusions in direct industry observation. We conducted in-depth interviews across the insulin biosimilar value chain, including active pharmaceutical ingredient suppliers, specialized biologic manufacturers, contract fill-finish and device formulators, and global specialty distributors. Interviews targeted decision-makers with direct commercial authority: VP-level Sourcing, Heads of Biologics R&D, Technical Operations Directors and Commercial Operations Leads.
| Stakeholder Role | Interview Share (%) |
|---|---|
| Sourcing & Procurement Leads | 35% |
| Biologics R&D Heads | 30% |
| Regulatory Affairs Managers | 20% |
| Commercial Operations Leads | 15% |
| Company Type | Representation (%) |
|---|---|
| Biologic API & Manufacturing | 40% |
| Contract Fill-Finish & Devices | 25% |
| Specialty Distributors | 20% |
| Hospital & Payer Groups | 15% |
Secondary validation draws on official multilateral trade and standards databases — UN Comtrade, WTO, US ITC and Eurostat — alongside corporate annual filings (10-K, SEC), investor presentations, patent databases and recognized non-profit technical standards and industry associations. Regulatory filings from the FDA and EMA inform approval-pathway analysis and interchangeability assessment.
We run simultaneous Top-Down and Bottom-Up modeling. Top-down allocates macroeconomic pharmaceutical expenditure and diabetes-care spend across insulin biosimilar segments and geographies. Bottom-up models manufacturer capacity, product pricing and end-use consumption by channel. The two estimates are reconciled against historical CAGR and demand elasticity.
| Dimension | Analytical Scope | Methodology Applied | Validation Level |
|---|---|---|---|
| Base-Year Market Size | Value in USD for base year | Bottom-up production & revenue triangulation | High |
| Forecast Horizon | Multi-year compound projection | Historical CAGR, regression analysis & demand elasticity | High |
| Regional Distribution | Regional share breakdown | Cross-border trade flow analysis & regional consumption | High |
| Competitive Landscape | Leading market players | Annual reports, capacity mapping & commercial filings | High |