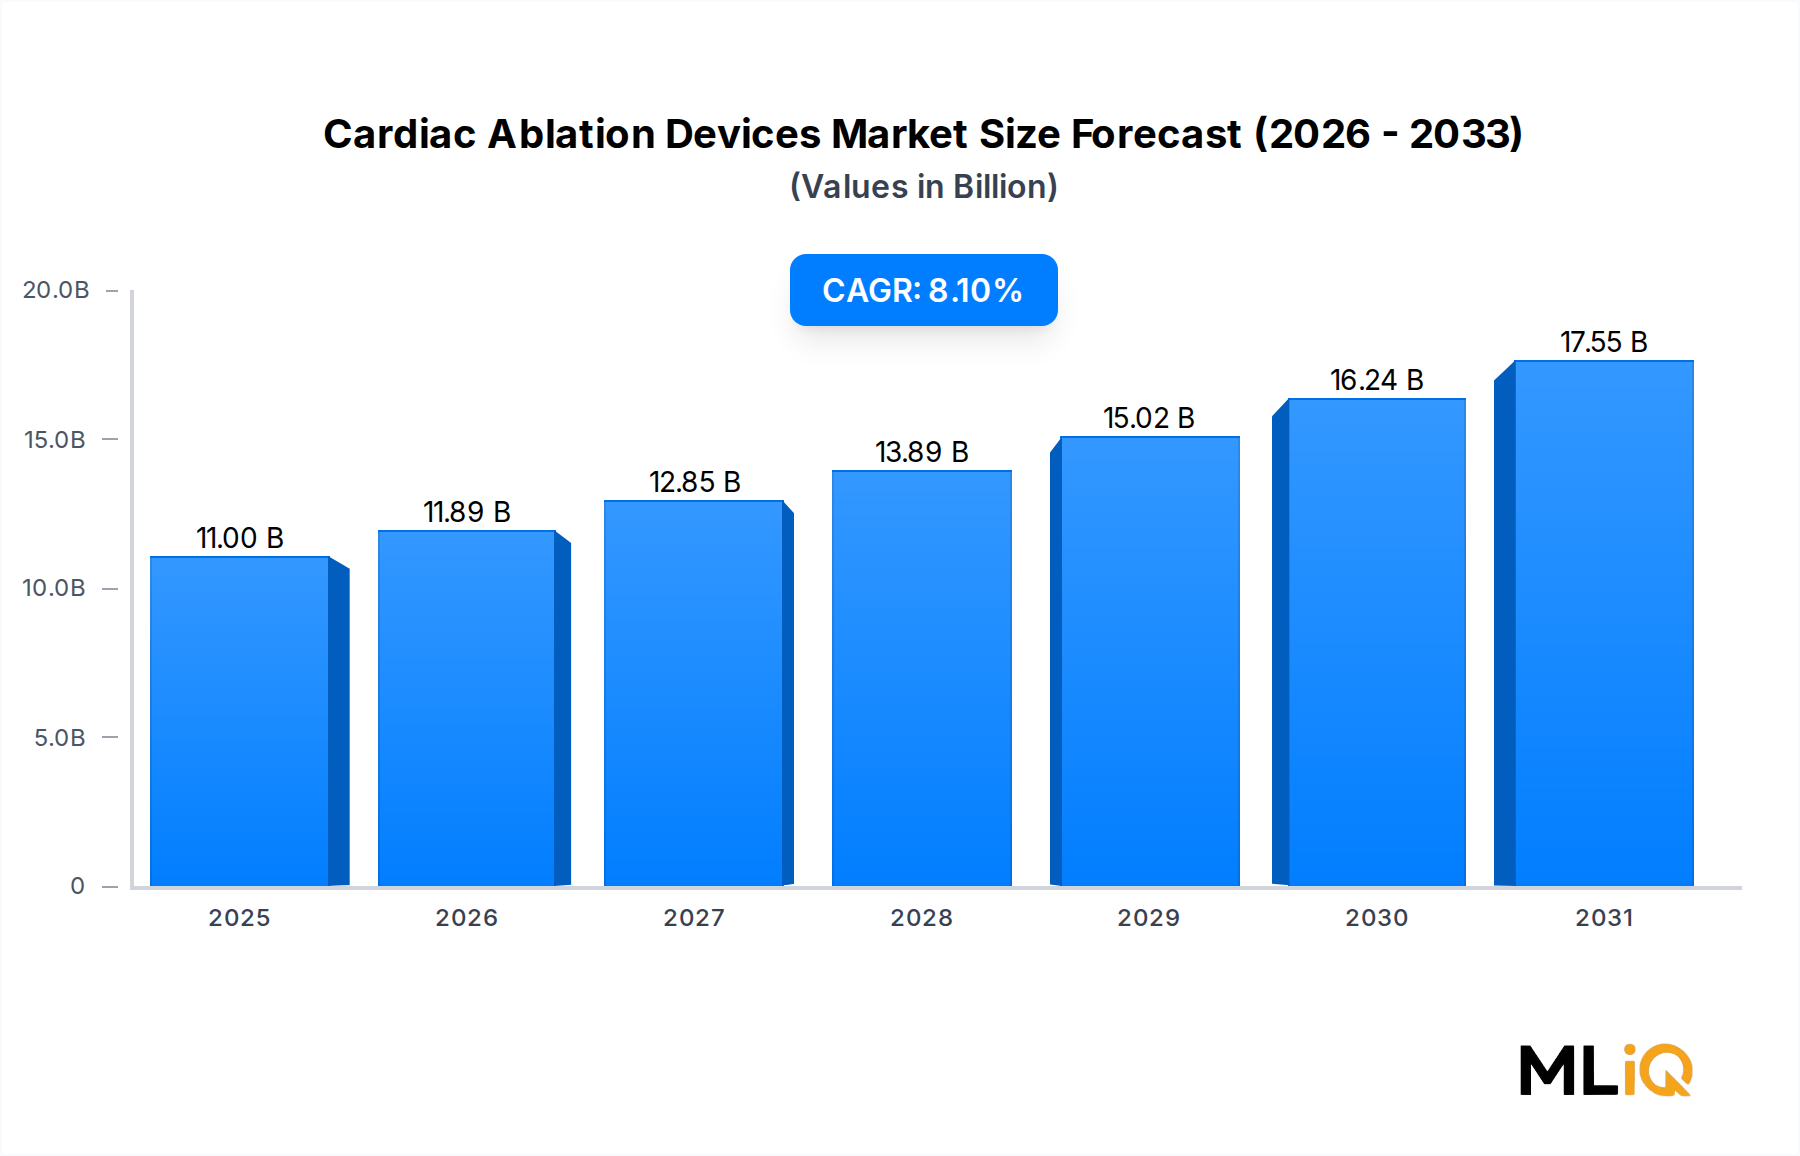
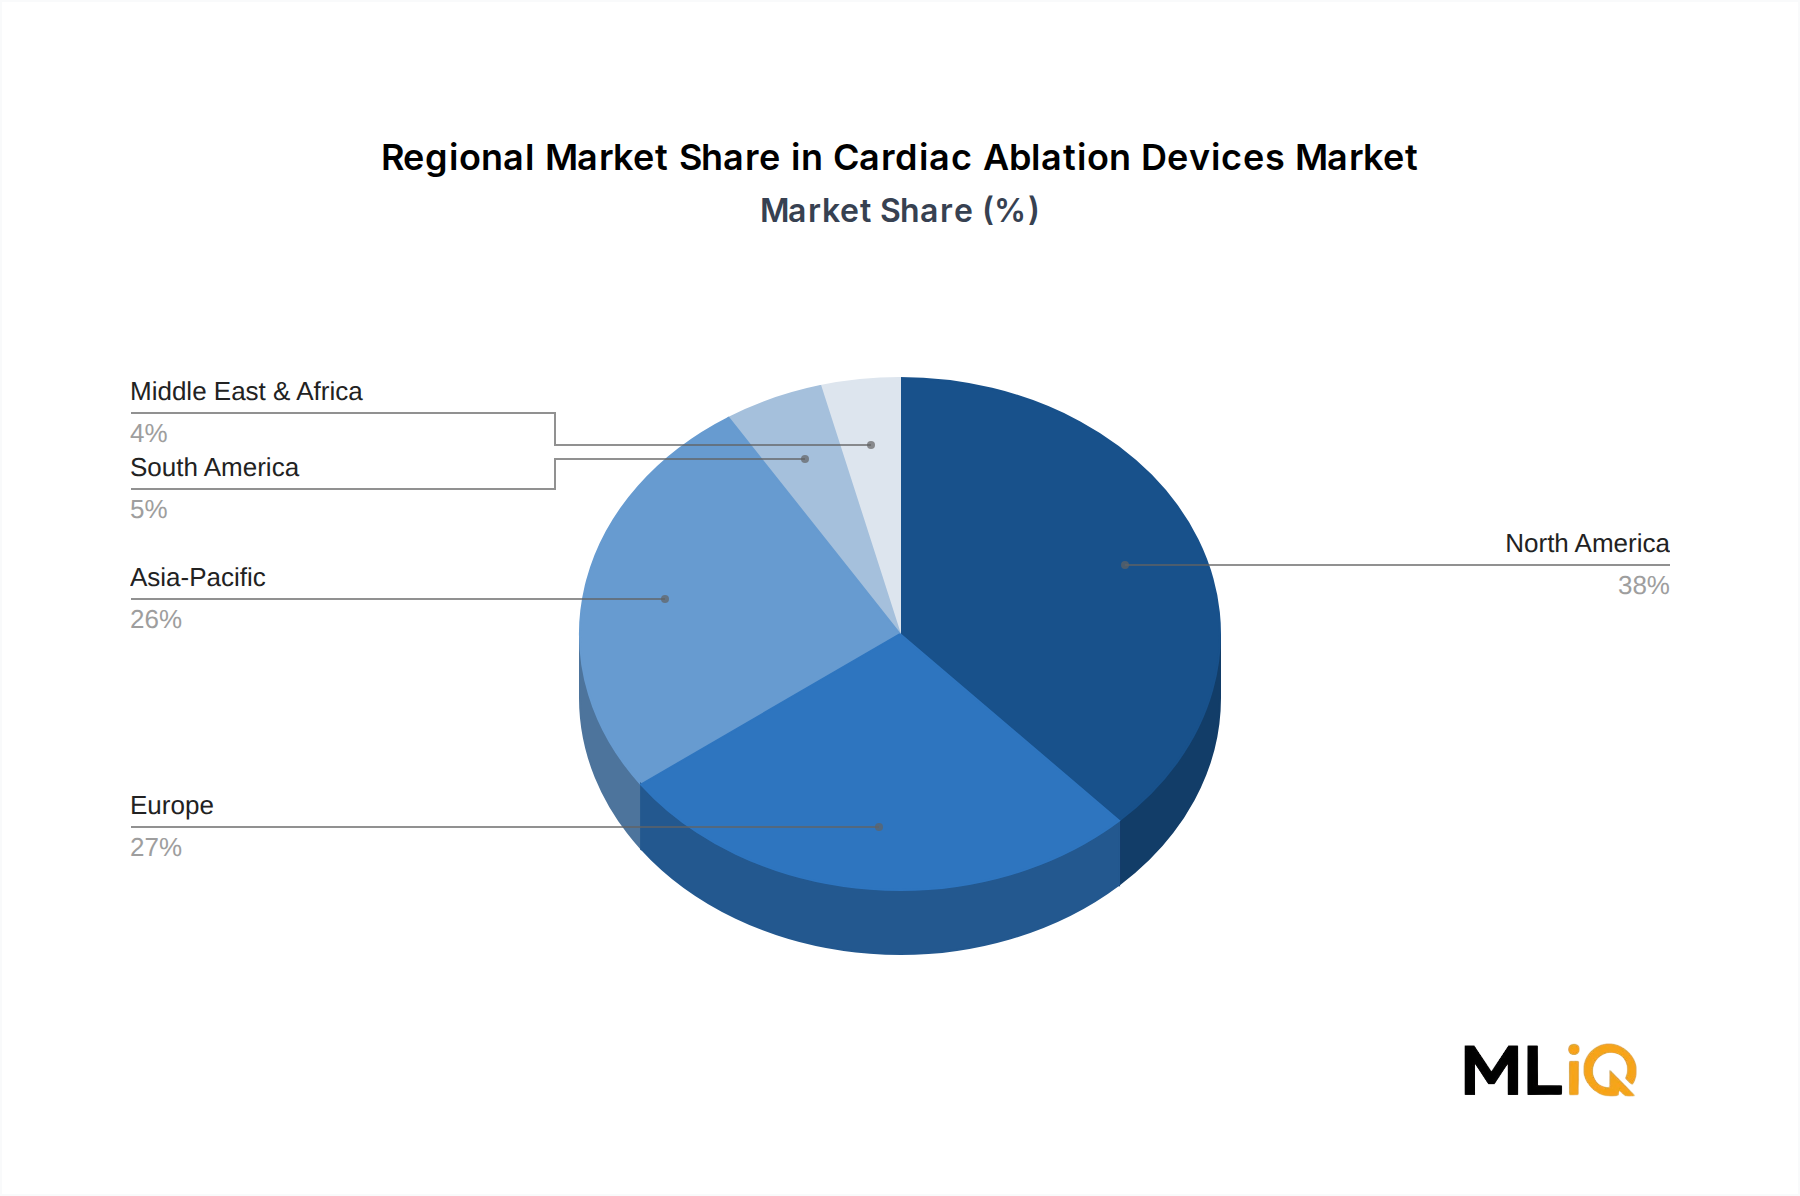
The Cardiac Ablation Devices Market is shaped by a set of quantifiable drivers and structural constraints that collectively determine the pace and geography of adoption.
Driver 1: Rising Atrial Fibrillation Prevalence. Atrial fibrillation affects approximately 59 million people globally as of recent epidemiological surveys, with incidence projected to increase by 40–50% by 2050 in developed markets due to aging demographics. This translates directly into growing procedural pipelines for electrophysiology laboratories, as AF represents the single largest application for ablation devices by procedure volume.
Driver 2: Shift Toward Rhythm Control. The landmark EAST-AFNET 4 trial demonstrated that early rhythm control — including ablation — reduces cardiovascular outcomes by 21% compared to rate control alone. This landmark evidence has accelerated guideline updates by the ESC and AHA, expanding the eligible patient population for ablation and creating a structural increase in referral rates from cardiology to electrophysiology programs.
Driver 3: Pulsed-Field Ablation Adoption. PFA systems, which received CE Mark and initial FDA approvals between 2021 and 2024, are driving capital equipment investment cycles at major electrophysiology centers. Early adopter hospitals are committing to PFA generator platforms, stimulating a parallel consumable catheter revenue stream that is expected to contribute meaningfully to market growth through 2030.
Constraint 1: Procedural Complexity and Training Barriers. Cardiac ablation procedures require specialized training periods of 12–24 months for operators to achieve independent competency, limiting the expansion of procedural capacity in markets with constrained electrophysiology workforce pipelines, particularly in South Asia, Latin America, and sub-Saharan Africa.
Constraint 2: Device and Procedure Costs. The total cost of an AF ablation procedure, including disposable catheters, mapping consumables, and facility fees, can range from $8,000 to $25,000 in high-income markets, creating access barriers in price-sensitive healthcare systems and constraining volume growth in middle-income geographies despite significant unmet clinical need.
Constraint 3: Complication Risk. Serious procedural complications — including cardiac tamponade (occurring in approximately 1–2% of cases), pulmonary vein stenosis, and atrioesophageal fistula — continue to influence physician risk-benefit calculations, particularly in less experienced centers, moderating procedure ramp-up rates.